Tesamorelin: abdominal imaging
The useful number here comes in square centimetres. It describes fat surrounding organs in adults with HIV and abdominal fat accumulation.
A cross-section of visceral fat
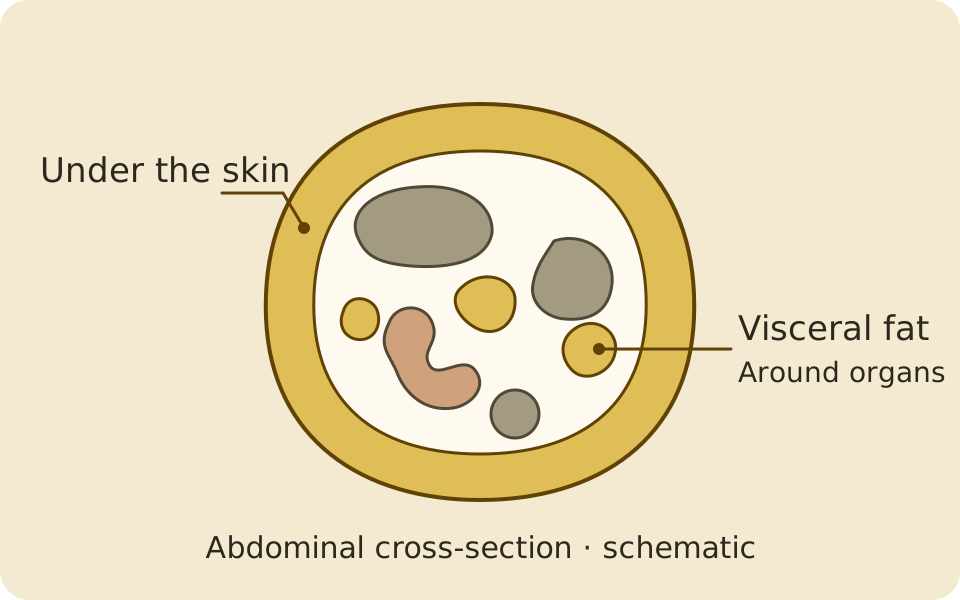
A six-month randomized trial in 50 adults receiving antiretroviral treatment for HIV found a tesamorelin treatment effect of −42 cm² in visceral fat compared with placebo. Visceral fat is the fat around internal organs. The area came from a belly scan, so the result describes a cross-section rather than pounds lost.
The unit does a surprising amount of work. The scan supplies an area inside the abdomen; a promised change in silhouette is much harder to justify. The participants had HIV and abdominal fat accumulation, the particular setting that gives this finding its medical meaning.
The same trial found a greater reduction in liver fat with tesamorelin than with placebo. That brings it into the same organ as the retatrutide liver substudy, with different participants and a different treatment.
The approved use
The LiverTox monograph records U.S. approval in 2010 for reducing excess abdominal fat in adults with HIV-associated lipodystrophy. Lipodystrophy refers to abnormal fat distribution. That approval has a specific population and purpose; it provides no general weight-loss indication.
The prescription medicine also comes with manufacturing, release, storage and medical-care controls. A laboratory sample bearing the same peptide name has its own unresolved questions. Identity testing addresses what is in a sample; it cannot confer the prescription medicine’s status.
I think the narrowness of the indication is useful information. It preserves the connection between the trial population and the use that was actually evaluated.
Hormone pulses
Tesamorelin is a modified analogue of growth hormone-releasing hormone. It stimulates the pituitary to release the body’s own growth hormone in pulses, with a rise in IGF-1, a growth-related protein made by the liver.
In a short study of 13 healthy men, overnight growth hormone and IGF-1 rose, while fasting glucose and insulin-stimulated glucose uptake showed no significant change. This short experiment gives a close look at the hormonal response. Its duration leaves blood-sugar safety over longer treatment unsettled.
The 52-week study in adults with HIV reported a sustained 18% reduction in visceral fat during treatment. Fat reaccumulated after discontinuation. Reaccumulation takes the shine off the initial decrease for me: the result depended on continuing treatment.
A 2026 meta-analysis of five randomized trials found reductions in visceral, trunk and liver fat and an increase in lean body mass. The pooled evidence remains rooted in HIV-associated lipodystrophy.
Safety beyond a favourable scan
The LiverTox assessment judged tesamorelin an unlikely cause of clinically apparent liver injury, with no reported attributable cases. That is a defined drug-safety judgment, rather than a conclusion about every possible adverse effect.
Growth-hormone stimulation and the rise in IGF-1 bring blood-sugar and growth-related safety questions. Long-term cancer evidence is limited; medical history matters. Tesamorelin is also prohibited in sport because of its hormone effects.
Reliable community accounts are absent from the material available here. Their absence establishes nothing about how often problems occur. That gap stays unfilled here; reassurance would require evidence. The measurement table returns to the distinction between a scan area, liver-fat proportion and body weight.